
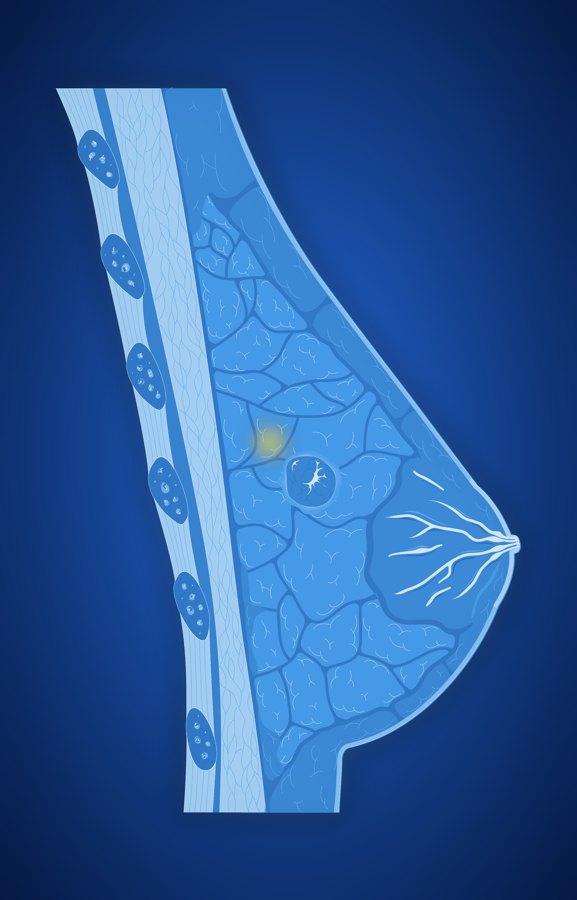

Breast cancer treatment is determined by more than tumour size. The pathology must define whether the cancer is invasive or in situ, its histological type and grade, estrogen and progesterone receptor status, HER2 status, nodal involvement and stage. These biological features can change whether surgery should occur first or whether systemic treatment should begin before surgery.
Modern breast cancer care aims not only to remove the tumour but also to preserve the breast, reduce unnecessary axillary surgery, minimize lymphedema, choose chemotherapy selectively, use targeted or endocrine therapy according to biology, and integrate reconstruction and radiotherapy when appropriate. For many early cancers, breast-conserving surgery followed by appropriate radiotherapy provides cancer control comparable to mastectomy.
International patients considering India should obtain a treatment sequence before travel. A quotation for mastectomy alone may be incomplete if the patient actually needs neoadjuvant chemotherapy, HER2-targeted therapy, sentinel-node staging, reconstruction or postoperative radiation. Conversely, not every patient requires chemotherapy or the most extensive operation.
A breast cancer diagnosis brings many decisions at once, often in a short time. This guide is written to help you understand the questions that matter, ask for a complete treatment sequence and judge whether travelling for treatment makes sense for you. It does not promise outcomes; every cancer and every patient is different.
Short Answer: Is India a Good Option for Breast Cancer Treatment?
For many patients, it can be. India has comprehensive breast cancer programmes that bring breast surgeons, oncoplastic and reconstructive surgeons, medical and radiation oncologists, pathology and breast imaging together, usually at a much lower private price than the USA, UK and Australia. But the first question is clinical rather than geographic: what are your subtype, stage and receptor results, and should treatment begin with surgery or with systemic therapy? A quotation for mastectomy alone may be incomplete. Rapidly progressive disease such as inflammatory breast cancer, uncontrolled infection or severe treatment side effects needs prompt local treatment, and travel should never delay important neoadjuvant therapy. Start with a remote review of your pathology, receptor results and breast imaging, and ask for the full treatment sequence before you book.
Quick Facts - Breast Cancer Treatment and Surgery for International Patients in India
| Topic | International-Patient Planning Point |
|---|---|
| Essential pathology | Invasive/in-situ type, grade, ER, PR, HER2 and other indicated biomarkers |
| Main biological groups | Hormone-receptor positive/HER2-negative, HER2-positive and triple-negative breast cancer |
| Surgery options | Breast-conserving surgery, oncoplastic surgery, mastectomy, nipple/skin-sparing approaches and reconstruction |
| Axillary staging | Sentinel-node biopsy is standard for many clinically node-negative patients; full dissection is selective |
| Treatment before surgery | Commonly considered for HER2-positive, triple-negative and selected locally advanced cancers |
| Radiotherapy | Usually follows breast conservation; indications after mastectomy depend on stage/pathology |
| Systemic therapy | Chemotherapy, endocrine therapy, HER2-targeted therapy, immunotherapy and selected targeted drugs |
| India stay | Often about 2-4 weeks for uncomplicated surgery; longer if reconstruction or treatment is initiated in India |
| India surgery cost | Broadly US$3,500-8,000 for many standard operations; complex reconstruction can raise cost substantially |
| Records to send | Biopsy/pathology, ER/PR/HER2, breast imaging, staging scans if done, treatment history and genetic/genomic reports |
| Major Indian hubs | Delhi NCR, Mumbai, Chennai, Bengaluru, Hyderabad and other tertiary breast oncology centres |
| Companion | Strongly advised throughout the stay and the journey home, especially after reconstruction or when drains and chemotherapy are involved |
Key principle: A bigger operation is not automatically a better cancer operation. The correct treatment combines adequate local control with biology-directed systemic therapy and preservation of function whenever oncologically safe.
Why India, Breast Cancer Biology and Diagnosis
Why Do International Patients Choose India for Breast Cancer Treatment?
Patients travel for breast cancer care for practical reasons, and the strongest ones are about reaching a coordinated team at a price that does not force a compromise on the plan:
- Lower cost. Private Indian hospitals often quote much less than self-pay prices in the USA, UK, Australia and other high-cost markets for surgery and radiation, although branded drugs may show a much narrower gap.
- Comprehensive breast programmes. Major cancer centres have breast surgeons, oncoplastic and reconstructive surgeons, medical and radiation oncologists, breast radiologists and pathologists working as one team.
- Breast conservation and reconstruction expertise. Oncoplastic techniques and the full range of implant and flap reconstruction are available at larger centres.
- Modern radiotherapy and systemic therapy. Image-guided radiation, shorter hypofractionated schedules, chemotherapy, HER2-targeted therapy, immunotherapy and endocrine treatment can often be delivered in one place.
- Multidisciplinary review. A tumour board can decide the sequence of surgery, systemic therapy and radiation before any operation is booked.
- Timely access. Patients facing long waits or limited local options can often be assessed promptly once the records are reviewed, though a hurried decision on incomplete pathology helps no one.
- International patient support and English-speaking teams. Major hospitals typically help with appointments, hospital letters for visas, airport pick-up and accommodation guidance.
- A plan you can review first. A remote review can state the subtype, stage and proposed sequence before you commit to travel, and may show that treatment close to home is the better choice.
Emergencies and Urgent Treatment Are Different
Fever during chemotherapy, rapidly worsening breast swelling or redness, breathlessness, chest pain, severe arm swelling, uncontrolled vomiting or dehydration, or rapidly progressive disease needs immediate local care. Do not delay urgent or neoadjuvant treatment to arrange international travel.
Patient Tip
Low cost should be the beginning of your evaluation, not the end of it. The sections that follow explain how to judge whether the proposed sequence is sensible, how to assess the team and how to compare the whole pathway rather than the surgery price alone.
How Does India Compare with Other Medical Travel Destinations?
Many patients also look at breast programmes abroad before deciding. There is no single best country for every patient; the right choice depends on where you live, your cancer and what you can verify about the team and hospital. These are the factors worth comparing:
| Factor | What to compare | How India generally fares |
|---|---|---|
| Cost | The full itemized pathway: surgery, reconstruction, drugs, radiation, tests and exclusions | Often much lower than self-pay pricing in Western countries for surgery and radiation; branded-drug savings vary widely |
| Team experience | Breast surgeon, oncoplastic and plastic surgery volume, and a genuine multidisciplinary tumour board | Major Indian centres have experienced breast teams; always verify surgeon and centre volume |
| Pathology and imaging | Receptor testing quality, breast MRI, image-guided biopsy and localization | Available at large cancer centres; confirm the specific hospital |
| Radiation and systemic therapy | Hypofractionated schedules, DIBH, HER2 drugs, immunotherapy and biosimilar policy | Often available in the same hospital; confirm for your case |
| Language | Whether doctors and nurses communicate easily with you | English is widely used by medical teams in major Indian hospitals |
| Distance and flight time | Length of the flight and the 2-5 weeks or more you may need to stay | Depends on where you live: relatively close for patients from South Asia, the Middle East and East Africa, and a long-haul journey from the Americas and parts of Europe |
| Visa | Visa type, processing time and attendant rules | India has a dedicated medical visa system with an attendant category; always confirm current rules for your nationality |
| Follow-up | Who will give ongoing systemic therapy, imaging and surveillance at home | Depends on the team; ask for a defined hand-over plan before you commit |
A Fair Way to Compare Destinations
- Ask every destination for the same itemized written plan (operation, axillary procedure, reconstruction, radiation, drugs and exclusions).
- Compare the clinical sequence first and the price second.
- Compare the total trip cost - treatment, a contingency for complications, flights, accommodation for weeks, companion and local transport.
- Judge the breast team and hospital, not just the country or the equipment.
- Compare the follow-up plan: who will give continuing treatment, imaging and surveillance at home?
What Is Breast Cancer?
Breast cancer arises from abnormal cells within breast ducts or lobules and includes multiple biological diseases. Most invasive cancers are carcinomas, but their receptor profiles and molecular characteristics differ substantially. Treatment should therefore be subtype-specific.
Ductal Carcinoma In Situ - DCIS
DCIS is a non-invasive malignancy confined to breast ducts. Treatment commonly involves breast-conserving surgery plus radiation or mastectomy when disease is extensive; endocrine risk-reduction may be considered for hormone-receptor-positive disease. Chemotherapy is not used for pure DCIS.
Invasive Ductal / No Special Type Cancer
This is the most common invasive breast cancer. Surgery, systemic therapy and radiation are selected according to tumour size, nodes, receptors, grade and patient factors. The term alone does not determine chemotherapy need.
Invasive Lobular Cancer
Lobular cancer can be more difficult to define on conventional imaging and may be multifocal or bilateral. MRI is useful selectively when extent is uncertain. Surgical principles are similar, but imaging-pathology concordance is important.
ER and PR Receptors
Estrogen and progesterone receptors indicate hormone sensitivity. Hormone-receptor-positive cancers commonly receive endocrine therapy and may or may not need chemotherapy depending on recurrence risk. Receptor percentage/intensity and menopausal status can influence decisions.
HER2 Status
HER2-positive cancers can respond strongly to HER2-targeted drugs. Accurate IHC and confirmatory in-situ hybridization when required are essential. For many stage II-III HER2-positive cancers, systemic therapy before surgery is preferred.
Triple-Negative Breast Cancer
Triple-negative cancer lacks ER, PR and HER2 expression. Chemotherapy is central, and immunotherapy is used in selected early and metastatic settings according to current indications. For many larger or node-positive early TNBCs, neoadjuvant treatment is important.
Breast Cancer Grade
Grade describes how abnormal and proliferative tumour cells appear. Higher grade generally suggests more aggressive biology but is interpreted alongside receptors, stage and other factors. Grade is not the same as stage.
Clinical Stage
Stage considers tumour size, nodal disease and distant metastases, with breast cancer staging also incorporating biological factors in modern systems. Clinical stage is established before definitive treatment. Pathological stage after surgery may differ.
Breast Imaging
Diagnostic mammography and ultrasound define the primary lesion and axillary nodes. MRI is useful selectively for occult extent, dense breasts, lobular cancer, high-risk screening, implant evaluation or response assessment. MRI should not be ordered automatically for every patient.
Image-Guided Core Biopsy
Core-needle biopsy usually provides sufficient tissue for histology and receptor testing before treatment. It is preferable to removing an unexplained breast lump without oncologic planning. Suspicious nodes can also be sampled.
Pathology Review Before Travel for International Patients in India for Breast Cancer
International patients should have pathology and receptor results reviewed when findings are discordant, incomplete or from a low-volume laboratory. A wrong HER2 or receptor classification can alter the entire treatment pathway. Slides/blocks may be needed for repeat testing.
Genetic Testing
Germline testing for BRCA1/2 and other genes is indicated based on age, family history, ancestry, tumour subtype and clinical criteria. Results can affect bilateral breast/ovarian risk management and selected systemic therapies. Testing should include genetic counselling.
Genomic Recurrence Assays
For selected hormone-receptor-positive/HER2-negative early cancers, validated multigene assays can help estimate recurrence risk and chemotherapy benefit. They are not interchangeable with hereditary genetic testing. Use depends on nodal status, menopausal status and clinical context.
Breast Cancer Subtypes at a Glance
| Group | Typical features | Treatment direction |
|---|---|---|
| Hormone-receptor positive / HER2-negative | ER and/or PR positive; usually the most common group | Endocrine therapy is central; chemotherapy depends on recurrence risk, sometimes guided by genomic testing |
| HER2-positive | HER2 over-expressed on IHC or in-situ hybridization | HER2-targeted therapy with chemotherapy; treatment before surgery is often preferred for stage II-III disease |
| Triple-negative | ER, PR and HER2 all negative | Chemotherapy is central; immunotherapy is used in selected settings; treatment before surgery is commonly considered |
| DCIS | Non-invasive, confined to ducts | Surgery with radiation or mastectomy; endocrine risk reduction may be considered; no chemotherapy for pure DCIS |
Making the Remote Review Count
- Send the biopsy and pathology reports, including ER, PR and HER2, and slides or blocks if the diagnosis is uncertain
- Send mammography, ultrasound and MRI images (not only reports) and any staging scans
- Include node biopsy results, genetic or genomic reports and exact details of any treatment already given
- If neoadjuvant therapy has started, include drugs, dates and response imaging
- Ask the team for the correct sequence of treatment before any surgery is quoted
Send your biopsy and pathology reports with ER, PR and HER2 results, mammogram, ultrasound and MRI images, any staging scans, node biopsy, genetic or genomic reports and details of any treatment already given. You will receive a preliminary opinion covering the subtype and stage, whether treatment should begin with surgery or systemic therapy, whether breast conservation or reconstruction is realistic, the radiotherapy and systemic-therapy plan, the stay in India, an itemized cost estimate and a follow-up plan, so you can decide with a clear picture in hand.
Treatment Sequencing: Surgery First or Treatment First
When Surgery Comes First
Many small operable hormone-receptor-positive/HER2-negative cancers proceed directly to surgery, followed by pathology-directed adjuvant treatment. The decision depends on tumour-to-breast ratio, nodes and whether preoperative therapy would change management.
When Treatment Should Come Before Surgery
Neoadjuvant chemotherapy plus targeted/immunotherapy is commonly used for selected HER2-positive and triple-negative cancers and for locally advanced disease. It can downstage breast/axilla and provide important response information. The post-treatment pathology can guide escalation or de-escalation of further therapy.
Pathological Complete Response
pCR means no residual invasive cancer in the breast and sampled nodes after neoadjuvant therapy according to defined criteria. It is prognostically important in HER2-positive and triple-negative disease. pCR does not eliminate all need for postoperative treatment.
Choosing the Sequence at a Glance
| Situation | Usual direction | Why it matters |
|---|---|---|
| Small, node-negative, hormone-receptor positive cancer | Surgery first is often reasonable | Final pathology and sometimes genomic testing then guide systemic therapy |
| HER2-positive stage II-III | Systemic therapy before surgery is often preferred | Response can guide later treatment |
| Triple-negative, larger or node-positive | Treatment before surgery is commonly considered | Response, including pathological complete response, guides further therapy |
| Locally advanced or inflammatory | Systemic therapy first, then surgery and radiation | Rapid local control and timely drugs are essential |
| Wish to conserve the breast but tumour is large | Treatment before surgery may shrink disease | May make breast conservation safer, though it is not guaranteed |
Breast and Axillary Surgery for International Patients in India
Breast-Conserving Surgery
Lumpectomy/wide local excision removes the tumour with an appropriate margin while preserving most breast tissue. It is usually followed by radiotherapy. Cosmetic outcome and tumour-to-breast ratio are part of planning.
Breast Conservation vs Mastectomy for International Patients in India
For appropriately selected early-stage patients receiving indicated radiotherapy, breast conservation provides survival outcomes comparable to mastectomy. Mastectomy may reduce local breast recurrence risk in some settings but does not automatically improve survival. Patient preference, genetics, extent and radiation feasibility matter.
Surgical Margins
For invasive cancer and DCIS, accepted margin standards differ. A close measurement does not automatically require mastectomy, and re-excision decisions depend on pathology and planned radiation. The pathology report should clearly document margin status.
Oncoplastic Breast Surgery
Oncoplastic techniques combine cancer excision with breast reshaping, allowing larger resections while preserving breast form in selected patients. Contralateral symmetrization may be considered. Tumour localization and postoperative radiation planning must be coordinated.
Mastectomy
Mastectomy removes most breast tissue and is used for extensive/multicentric disease, unsuitable breast conservation, selected genetic-risk situations or patient preference after informed discussion. It does not automatically remove the need for radiation or systemic therapy.
Skin-Sparing Mastectomy
Most breast skin is preserved while glandular tissue is removed, facilitating immediate reconstruction. It is suitable for selected patients when skin is not involved by tumour. Oncologic safety depends on proper selection.
Nipple-Sparing Mastectomy
The nipple-areolar complex may be preserved when tumour location, imaging and intraoperative/pathological assessment support safety. Nipple sensation can be reduced or lost. Not every tumour or breast anatomy is suitable.
Contralateral Prophylactic Mastectomy
Removing a healthy opposite breast can reduce new contralateral breast cancer risk but usually does not improve survival for average-risk women with unilateral cancer. It may be appropriate for selected hereditary-risk patients. The decision should not be driven by fear alone.
Sentinel Lymph-Node Biopsy for International Patients in India for Breast Cancer
A tracer identifies the first draining axillary nodes for pathological assessment. This allows many clinically node-negative patients to avoid full axillary dissection. Technique and indications vary after neoadjuvant therapy.
Axillary Lymph-Node Dissection
ALND removes more axillary nodes and is now reserved for selected node-positive scenarios. It provides regional control but increases lymphedema, numbness and shoulder morbidity. Modern breast oncology seeks to avoid unnecessary ALND.
Axillary Surgery After Neoadjuvant Therapy
Patients whose biopsy-proven nodal disease responds to systemic therapy may be eligible for targeted axillary staging rather than automatic full dissection in selected settings. Clip placement in the biopsied positive node before treatment can assist later surgery.
Lymphedema
Arm swelling can occur after lymph-node surgery and/or regional radiation. Risk is lower after sentinel-node biopsy than full dissection. Early recognition, physiotherapy, compression and specialist management can reduce progression.
Surgery Options at a Glance
| Option | What it involves | Points to ask |
|---|---|---|
| Breast-conserving surgery (lumpectomy) | Removes the cancer with a margin and keeps the breast | Usually followed by radiotherapy; ask about margins and re-excision |
| Oncoplastic surgery | Cancer removal with breast reshaping | Can allow conservation in larger tumours and improve shape |
| Mastectomy | Removal of breast tissue | Ask whether radiation may still be needed afterwards |
| Skin- or nipple-sparing mastectomy | Preserves the skin envelope or nipple when oncologically safe | Suitability depends on tumour position, size and breast shape |
| Sentinel-node biopsy | Samples the first draining nodes | Standard for many clinically node-negative patients |
| Axillary dissection | Removes more axillary nodes | Selective; raises lymphedema risk, so ask why it is needed |
Breast Reconstruction for International Patients in India
Immediate Breast Reconstruction
Reconstruction can begin at the time of mastectomy using an implant/expander or autologous tissue. The likelihood of postoperative radiation influences the reconstruction strategy. Cancer treatment should not be delayed by avoidable reconstruction complications.
Delayed Reconstruction
Reconstruction can be performed after chemotherapy/radiation and recovery. This may simplify oncologic treatment for selected patients who are likely to require chest-wall radiation. Delayed reconstruction remains a valid option, not inferior care.
Implant-Based Reconstruction
Implants avoid a donor-site operation and can shorten surgery, but infection, capsular contracture, implant loss and future revision are possible. Radiation increases some implant complications. Long-term maintenance should be discussed.
Autologous Flap Reconstruction
DIEP, TRAM, latissimus and other flaps use the patient's tissue. They involve longer surgery but can provide durable natural reconstruction, especially in selected irradiated patients. Microsurgical expertise and donor-site considerations matter.
Reconstruction Options at a Glance
| Option | What it involves | Points to ask |
|---|---|---|
| Immediate reconstruction | Done at the time of mastectomy | Ask how it interacts with the possible need for radiation |
| Delayed reconstruction | Done after cancer treatment is complete | May require a longer stay or a second trip |
| Implant-based | Expander or implant, sometimes with a mesh or tissue support | Ask about implant type, source and warranty |
| Autologous flap | Uses your own tissue, sometimes microsurgical | Longer operation and recovery; confirm surgeon experience |
Radiotherapy
Radiotherapy After Breast Conservation for International Patients in India
Whole-breast or selected partial-breast radiation reduces local recurrence after lumpectomy. Hypofractionated schedules allow many patients to complete treatment in fewer weeks. Radiation omission is appropriate only in selected low-risk scenarios.
Post-Mastectomy Radiotherapy
Chest-wall and regional nodal radiation may be recommended for node-positive, large, margin-positive or other high-risk disease. Mastectomy does not guarantee radiation avoidance. Reconstruction planning should anticipate this possibility.
Deep Inspiration Breath Hold
For selected left-sided breast radiation, DIBH moves the heart away from the chest wall and can reduce cardiac dose. Modern planning should quantify heart and lung exposure.
Systemic Therapy for International Patients in India for Breast Cancer
Chemotherapy
Chemotherapy is recommended when expected recurrence reduction justifies toxicity. Regimens depend on subtype, stage and prior treatment. Not every early breast cancer needs chemotherapy.
HER2-Targeted Therapy
HER2-positive cancers are treated with HER2-directed agents according to stage and setting, often combined with chemotherapy. Cardiac monitoring is commonly required. Residual disease after neoadjuvant treatment can change postoperative targeted therapy.
Immunotherapy
Checkpoint inhibition is incorporated into treatment of selected triple-negative cancers, including certain high-risk early and metastatic settings. It can cause immune-mediated endocrine, lung, bowel, liver and other toxicities. Indication depends on disease setting and protocol.
Endocrine Therapy
Tamoxifen, aromatase inhibitors and ovarian suppression are used according to menopausal status, recurrence risk and tolerance. Treatment often continues for years. Bone health, menopausal symptoms and adherence require attention.
CDK4/6 and Other Targeted Therapies
Targeted agents are used in selected hormone-receptor-positive disease and other molecularly defined settings. Indications differ between early and metastatic cancer. Drug selection should follow evidence and biomarker context.
Bone-Modifying Therapy
Bisphosphonates or denosumab may be used for bone metastases, treatment-related bone loss or selected adjuvant settings. Dental health and calcium/vitamin D status may require assessment. Jaw osteonecrosis risk requires appropriate precautions.
Systemic Therapy at a Glance
| Treatment | Mainly used for | Points to ask |
|---|---|---|
| Chemotherapy | Triple-negative, HER2-positive and higher-risk hormone-receptor positive cancers | Is it needed for my subtype and stage, and can it be given before surgery? |
| HER2-targeted therapy | HER2-positive cancers | Which drug, biosimilar policy and cardiac monitoring plan? |
| Immunotherapy | Selected triple-negative settings | Is it indicated in my case, and who will give it at home? |
| Endocrine therapy | Hormone-receptor positive cancers | Which drug and for how many years, and who will monitor it? |
| CDK4/6 and other targeted drugs | Selected hormone-receptor positive and advanced cancers | What does the evidence show for my stage? |
| Bone-modifying therapy | Selected patients at bone risk | Is a dental check needed first? |
Special Situations
Fertility Preservation for International Patients in India for Breast Cancer
Chemotherapy can impair ovarian reserve. Young patients should discuss egg/embryo preservation or other options before systemic treatment when this can be done without unsafe delay. Pregnancy-related plans should be coordinated with oncology.
Pregnancy and Breast Cancer
Breast cancer during pregnancy requires trimester-specific coordination of surgery and systemic therapy. Radiotherapy and several drugs are deferred until appropriate. Pregnancy itself does not automatically require termination.
Young Women With Breast Cancer
Younger patients more often require genetic assessment and may have biologically aggressive subtypes. Fertility, premature menopause, body image and long-term survivorship deserve early attention. Age alone should not dictate bilateral mastectomy.
Older Patients
Treatment should reflect physiological fitness, tumour biology, life expectancy and patient goals rather than age alone. Some low-risk hormone-sensitive cancers can be managed with less intensive local/systemic treatment. Frailty assessment can improve decisions.
Locally Advanced Breast Cancer
Large tumours, skin/chest-wall involvement or bulky nodes usually require systemic treatment before surgery. Response can convert some patients to operability or breast conservation. Inflammatory breast cancer requires a distinct multimodality approach.
Inflammatory Breast Cancer
Inflammatory breast cancer presents with rapid breast swelling, redness and skin edema and is treated with systemic therapy first, followed by mastectomy and radiation when responsive. Upfront breast-conserving surgery is generally not the standard pathway.
Metastatic Breast Cancer Care for International Patients in India
Stage IV breast cancer is primarily treated with systemic therapy selected by subtype. Surgery/radiation can control symptoms or selected local problems; aggressive local treatment is individualized. The presence of metastases changes treatment goals and sequencing.
Oligometastatic Disease
A small number of metastases may sometimes be treated with surgery or stereotactic radiation in highly selected patients, but systemic biology remains central. This should be discussed in a multidisciplinary setting.
Local Recurrence
Recurrence in the breast/chest wall or regional nodes requires restaging and biopsy to reassess receptors. Surgery, radiation and systemic therapy depend on previous treatment and extent. Receptor status can change at recurrence.
Breast Cancer After Previous Radiation
A new tumour or recurrence after prior breast radiation requires individualized local treatment. Mastectomy is common, though selected re-irradiation strategies exist at specialized centres. Previous dose records are important.
Rehabilitation, Body Image and Surveillance
Rehabilitation After Surgery for International Patients in India for Breast Cancer
Shoulder range-of-motion exercises, scar management, lymphedema education and gradual return to activity support recovery. Axillary procedures and reconstruction influence the programme. Persistent shoulder restriction should be treated early.
Psychosexual and Body-Image Recovery
Breast loss, scars, endocrine symptoms and early menopause can affect self-image and intimacy. Reconstruction, prostheses, counselling and sexual-health support are legitimate components of survivorship. These issues should not be dismissed as cosmetic.
Surveillance After Treatment
Follow-up includes clinical review and breast imaging according to remaining breast tissue and risk. Routine whole-body scans are not automatically required in asymptomatic early-stage survivors. New persistent symptoms should be evaluated promptly.
Preparing Yourself Before Breast Cancer Surgery (Prehab)
Preparation helps recovery. Always agree what is appropriate with your surgical team, and never let preparation delay urgent cancer treatment:
- Ask about gentle arm and shoulder range-of-motion exercises, and learn them before surgery
- Ask for lymphedema awareness teaching, including how to protect the arm and what early swelling looks like
- A dental check before bone-modifying drugs, if these may be used
- A fertility discussion before systemic therapy, where relevant
- Stopping smoking and limiting alcohol, which supports healing, especially after reconstruction
- Daily walking and general fitness as advised by your team
- A medicine review, including blood thinners, hormone treatments, supplements and herbal products
- Good nutrition and a plan for sleep and emotional support
- Practical arrangements for you and your companion, including comfortable front-opening clothing
Preparation should never delay urgent cancer treatment. Your team will tell you if time is critical.
Around Breast Cancer Treatment: What to Expect
| Stage | What usually happens |
|---|---|
| Before treatment | Pathology and imaging review, receptor results, staging where indicated, tumour-board sequencing, genetic counselling where relevant, fertility discussion and consent covering the operation, axillary procedure and reconstruction |
| Surgery | Breast operation with sentinel-node biopsy or other axillary surgery, with reconstruction if planned; some patients go home within a few days |
| Early recovery in India | Wound and drain checks, arm exercises, final pathology review and the decision on radiation and systemic therapy |
| Further treatment | Radiotherapy, chemotherapy, HER2-targeted or endocrine therapy as recommended, in India or at home |
| After you return home | Gradual return to normal activity, breast imaging and oncology follow-up on a written schedule |
Choosing Your Surgeon, Centre and City
Choosing a Breast Cancer Surgeon for International Patients in India
Look for a surgeon whose practice includes breast oncology, sentinel-node techniques, oncoplastic options and coordination with reconstruction. Ask about breast-conservation rates where appropriate, re-excision policy and axillary de-escalation. A surgeon who offers only mastectomy may not provide the full range of modern breast-conserving options.
Choosing a Comprehensive Breast Cancer Centre
The centre should integrate breast imaging, image-guided biopsy, pathology with ER/PR/HER2 testing, surgical oncology, medical oncology, radiation oncology, genetics, reconstruction, nuclear medicine and rehabilitation. Multidisciplinary review is particularly valuable before neoadjuvant therapy or complex reconstruction.
Major Breast Cancer Treatment Hubs for International Patients in India
Delhi NCR, Mumbai, Chennai, Bengaluru, Hyderabad and other tertiary centres provide comprehensive breast oncology, oncoplastic surgery, reconstruction and modern systemic/radiation therapy. The best destination depends on disease subtype and required expertise rather than city alone.
Warning Signs of an Unreliable Offer
Medical travel works best when the information you receive is specific, itemized and clinically sensible. Be cautious if you see any of the following:
Red Flags
- A mastectomy recommendation or fixed surgery date before receptor status and stage are known
- No discussion of whether treatment should begin before surgery, when your subtype suggests it should be considered
- Promises of a 'cure', 'guaranteed' results or 'no recurrence'
- Advice to omit indicated radiation or systemic therapy to shorten your stay
- A quotation for surgery alone, with no mention of axillary surgery, radiation, drugs or reconstruction
- Recommending the largest operation, such as removal of the healthy breast, without explaining the evidence
- No breast radiologist, pathologist, medical oncologist or radiation oncologist involved in the plan
- Pressure to decide or pay quickly, or a base price with unclear exclusions for complications and re-excision
- No plan for continuing treatment, imaging and surveillance after you return home
What a Good International Patient Service Should Provide
A well-run programme should make the journey easier at every stage:
- A named coordinator and a direct line to the clinical team before you travel
- Review of your actual pathology and imaging by the treating team, and a written preliminary opinion covering the subtype, stage, proposed sequence and surgical options
- Honest discussion of alternatives, including treatment closer to home, and whether travel is necessary at all
- An itemized written estimate that states what is included, how reconstruction, implants, drugs, radiation and complications are charged
- A hospital letter for your medical visa application, and guidance for attendant visas
- Airport pick-up, assistance on arrival and accommodation near the hospital for weeks
- Interpreter support where needed
- Final pathology with receptor results, operative report, discharge summary, radiation and systemic-therapy recommendations and surveillance schedule
- A defined follow-up pathway after you return home, including teleconsultations with the treating team
Cost, Packages and Quotations for International Patients in India for Breast Cancer
Indicative Breast Cancer Treatment and Surgery Costs in India
| Treatment / Procedure | Broad International-Patient Planning Range |
|---|---|
| Breast-conserving surgery + sentinel node | Approx. US$3,500-6,000 |
| Mastectomy + sentinel node / axillary surgery | Approx. US$3,500-7,000 |
| Oncoplastic breast-conserving surgery | Approx. US$4,500-8,000 |
| Mastectomy + implant reconstruction | Approx. US$6,000-12,000+ |
| Autologous / microsurgical reconstruction | Approx. US$10,000-20,000+ |
| Chemotherapy | Approx. US$500-3,000+ per cycle; drug dependent |
| HER2-targeted / immunotherapy | Can add thousands of US$ per dose/cycle; brand/biosimilar dependent |
| Breast / regional nodal radiotherapy | Approx. US$3,000-7,000+ |
| Genetic / genomic testing | Approx. US$300-4,000+ depending on test |
These are broad private international-patient planning estimates, not guaranteed tariffs. Reconstruction type, imported implants, chemotherapy drugs, targeted agents, immunotherapy, genomic assays, radiation technique and complications can substantially alter total cost.
What a Breast Cancer Surgery Package Should Include
Request the exact operation, sentinel-node tracer/procedure, axillary surgery if needed, oncoplastic/reconstruction fees, implants or flap surgery, anaesthesia, operating theatre, hospital stay and final pathology including receptor testing when required. Clarify whether postoperative oncology consultations are included.
Factors That Increase Total Breast Cancer Cost
Bilateral surgery, microsurgical reconstruction, prolonged admission, re-excision, imported implants, chemotherapy, HER2-targeted drugs, immunotherapy, genomic testing and radiotherapy can raise total treatment cost. Comparing only the surgery package can therefore be misleading.
Breast Cancer Treatment Cost - India vs USA, UK and Australia
| Representative Treatment | India | USA | UK Private | Australia Private | Approx. India Saving* |
|---|---|---|---|---|---|
| Lumpectomy /mastectomy + node surgery | $3.5k-7k | $25k-70k+ | $15k-30k+ | $18k-35k+ | Approx. 50-95% |
| Mastectomy + reconstruction | $6k-20k+ | $50k-150k+ | $25k-60k+ | $30k-70k+ | Approx. 20-95% |
| Breast radiotherapy course | $3k-7k | $15k-45k+ | $10k-25k+ | $12k-30k+ | Approx. 30-90% |
| Selected chemotherapy cycle | $0.5k-3k+ | $3k-15k+ | $1.5k-6k+ | $2k-7k+ | Approx. 0-97% |
*Broad private/self-pay planning comparisons only. Patented HER2-targeted, immunotherapy and other branded drugs may have much narrower price differences between countries. Exact savings require like-for-like treatment and drug comparison.
Budgeting for the Whole Pathway, Not Just the Operation
The operation is only one part of the budget. Ask for the treatment quotation, then add:
- Radiotherapy, chemotherapy, HER2-targeted, immunotherapy or endocrine drugs, and any genetic or genomic tests that are not in the surgical package
- A contingency for complications, re-excision, prolonged admission or reconstruction revision
- Return flights for you and your companion, with flexibility to change dates if recovery is slow
- Accommodation near the hospital for the whole stay, commonly about 2-5 weeks and longer if radiation or chemotherapy starts in India
- Meals, local transport and airport transfers
- Visa fees, travel insurance and any attendant visa costs
- Compression sleeve, surgical bras, drain supplies and rehabilitation or lymphedema therapy
- Follow-up imaging and tests at home
Breast Cancer Treatment Quotation Comparison Table
| Item | Centre A | Centre B |
|---|---|---|
| Pathology / subtype | ||
| Clinical stage | ||
| Neoadjuvant treatment | ||
| Breast operation | ||
| Sentinel / axillary surgery | ||
| Oncoplastic / reconstruction | ||
| Implant / flap costs | ||
| Final pathology | ||
| Chemotherapy | ||
| HER2 / immunotherapy | ||
| Radiotherapy | ||
| Genetic / genomic tests | ||
| Expected India stay | ||
| Total pathway estimate |
Your Journey: Records, Travel, Visa and Going Home
Remote Breast Cancer Case Review Before Travel
Send biopsy/pathology, ER/PR/HER2 results, mammography/ultrasound/MRI images, staging scans if performed, node biopsy, genetic/genomic reports and previous treatment. If neoadjuvant therapy has started, include exact drugs/dates and response imaging. The team should determine the correct sequence before quoting surgery.
Records Checklist
- Biopsy and pathology reports with ER, PR and HER2; slides or blocks if uncertain
- Mammography, ultrasound and MRI images, not only reports
- Staging scans and node biopsy results
- Genetic and genomic reports
- Exact drugs, doses, dates and response imaging if treatment has started
- Medicine list, allergies and other conditions, including heart history
- Details of any previous surgery or radiation
- Passport copy
Questions the Pre-Travel Opinion Should Answer
What is the subtype and clinical stage? Should treatment begin with surgery or systemic therapy? Is breast conservation oncologically safe? What axillary procedure is needed? Is reconstruction appropriate now or later? Will radiation be required? What systemic therapy is expected after surgery? These answers determine both travel duration and realistic total cost.
International Patient Treatment Journey
1) Remote pathology/imaging review. 2) multidisciplinary sequencing. 3) neoadjuvant therapy first when indicated. 4) travel/restaging. 5) breast/axillary surgery with reconstruction if appropriate. 6) final pathology. 7) adjuvant systemic/radiation decision. 8) rehabilitation. 9) fit-to-fly. 10) long-term surveillance at home. Patients receiving neoadjuvant treatment should have tumour/node localization planned before therapy when necessary.
How Long to Stay in India
Uncomplicated lumpectomy or mastectomy may allow an international stay of roughly 2-3 weeks; reconstruction can require 3-5 weeks or longer. If radiotherapy or chemotherapy is initiated in India, the stay may extend substantially. Final pathology should be reviewed before departure whenever it will alter immediate treatment.
Flying After Breast Cancer Surgery
Fitness depends on wound healing, drains, reconstruction, mobility and thrombosis risk. Many patients can fly after early recovery, but long-haul travel should be individualized. Patients travelling with a drain need explicit instructions and local backup.
Airline and Travel Practicalities After Breast Cancer Surgery
Airline rules differ, so confirm each point with your airline before you fly:
| Topic | What to arrange |
|---|---|
| Fit-to-fly letter | Ask your surgeon for written clearance stating the diagnosis, operation and date, and carry it in hand luggage |
| Blood clots | Cancer, surgery and chemotherapy raise clot risk; ask whether stockings or blood-thinning injections are needed, and walk and hydrate regularly in flight |
| Arm on the operated side | Ask your team and lymphedema therapist about a compression sleeve, arm care and carrying luggage; ask someone to lift bags |
| Drains and wounds | Confirm that drains have been removed or are safe for travel; carry dressings, wound-care instructions and drain-care supplies if advised |
| Implant or expander | Ask about any restrictions after expander or implant surgery, and carry the implant card and operative details |
| Low blood counts | If you are on chemotherapy, ask whether counts allow flying, and use a mask and hand hygiene as advised |
| Medicines and injections | Keep all medicines, injections and painkillers in hand luggage with a prescription list and a letter for needles or syringes if needed |
| Seat choice and assistance | An aisle seat helps movement and toilet access; request airport assistance if you tire easily |
| Records | Carry final pathology with ER/PR/HER2, operative report, discharge summary and contact details of the treating team |
| Flexible tickets and insurance | Book a flexible return so that a delay in healing does not mean losing money, and check what travel insurance covers for surgery-related complications |
Accommodation and Companion
A companion is strongly advised during surgery and early recovery, for help with drains, wound care, arm mobility, medicines and decisions, and during chemotherapy or radiation if these start in India. Accommodation should be close to the hospital so that fever, wound problems or other concerns can be reviewed promptly.
Medical Visa and Travel Planning for International Patients in India for Breast Cancer
Confirm current Indian medical-visa requirements through official channels, including the attendant visa for your companion. Carry the hospital invitation, a medical summary, your pathology and imaging and your medicines, and keep the visa duration and return travel flexible in case recovery or radiation takes longer than planned.
Continuing Chemotherapy or Targeted Therapy at Home
Obtain the exact regimen, doses, cycle dates, supportive medicines, cardiac-monitoring requirements and pathology/molecular reports. Confirm drug availability and whether biosimilar substitution is acceptable with the treating oncologist. Treatment continuity should be arranged before leaving India.
Radiotherapy Logistics for International Patients
Radiation can often be completed in India using shorter evidence-based hypofractionated schedules when appropriate, or arranged at home. The radiation oncologist should provide target and dose recommendations if treatment is transferred. Do not omit indicated radiation simply to shorten travel.
Post-Return Follow-Up
Carry final pathology, operative report, receptor results, systemic-treatment summary, radiation recommendation/summary, reconstruction details and surveillance plan. Establish local oncology and breast imaging follow-up. Teleconsultation can complement local care.
Arranging Your Follow-Up Care at Home Before You Leave
Treatment and surveillance continue for years, so set up your home team before you travel and confirm it again before you fly home:
| Who | Role |
|---|---|
| Local medical oncologist | Gives or continues chemotherapy, HER2-targeted, immunotherapy or endocrine therapy and monitors blood tests and side effects |
| Radiation oncologist | Delivers or reviews radiation, using the target and dose recommendations from India |
| Breast imaging service | Carries out mammography, ultrasound or MRI on the agreed schedule, comparing with earlier images |
| Lymphedema therapist and physiotherapist | Support arm and shoulder movement, compression and early management of swelling |
| Plastic or reconstructive surgeon | Reviews implants, expanders or flaps, and plans any later reconstruction or revision |
| General practitioner | Coordinates care, general health, bone health, medicines and referrals |
| Emotional-support and counselling services | Support body-image, intimacy, fertility and mood concerns during and after treatment |
| Overseas treating team | Teleconsultations, review of scans and records, and advice on the plan |
Hand-over Checklist
- Written fit-to-fly clearance
- Final pathology with ER, PR and HER2
- Operative report and discharge summary
- Adjuvant systemic and radiation recommendations
- Reconstruction details, including implant information
- Exact drug regimen, doses and cycle dates
- Medicine list and cardiac-monitoring requirements
- Rehabilitation and arm-care instructions
- Surveillance schedule and next appointments
- Home oncologist details and emergency plan
Warning Signs
Urgent assessment is required for high fever, rapidly increasing breast/axillary swelling, wound redness/drainage, severe arm swelling, breathlessness, chest pain, uncontrolled vomiting/dehydration or fever during chemotherapy. Emergency symptoms require local assessment rather than waiting for an overseas response.
Do Not Wait for an Overseas Reply
Fever during chemotherapy, rapidly worsening breast swelling or redness, a wound that opens or discharges, severe arm swelling, breathlessness, chest pain or uncontrolled vomiting needs emergency care where you are. Tell the emergency team about your diagnosis and treatment, show your records, and contact your treating team afterwards.
Tools: Questions, Candidacy, FAQ and Checklist for International Patients in India for Breast Cancer
Twenty Questions to Ask the Breast Cancer Team
- 1What is my exact histological diagnosis?
- 2What are my ER, PR and HER2 results?
- 3What is my clinical stage?
- 4Do I need genetic testing?
- 5Do I need a genomic recurrence assay?
- 6Should I receive treatment before surgery?
- 7Am I suitable for breast-conserving surgery?
- 8Would mastectomy improve survival in my case?
- 9Can oncoplastic surgery improve conservation/cosmesis?
- 10Do I need sentinel-node biopsy or axillary dissection?
- 11If a node is positive before chemotherapy, will it be clipped?
- 12Am I suitable for nipple- or skin-sparing mastectomy?
- 13Should reconstruction be immediate or delayed?
- 14Will I need radiotherapy after surgery?
- 15Will I need chemotherapy?
- 16Will I need HER2-targeted or immunotherapy?
- 17Will I need long-term endocrine therapy?
- 18What exactly is included in the quotation?
- 19How long should I remain in India?
- 20What follow-up and breast imaging will I need at home?
Who Is a Good Candidate for Breast Cancer Medical Travel?
A suitable patient is medically stable, has sufficient pathology/imaging for a meaningful treatment plan and can remain in India through the necessary surgery and early recovery. Travel can be especially useful when breast conservation, oncoplastic surgery, complex reconstruction or coordinated multidisciplinary treatment is not readily available locally.
When Travel Should Not Delay Treatment
Rapidly progressive inflammatory breast cancer, uncontrolled infection, severe treatment toxicity or other urgent problems require timely local stabilization and systemic therapy. Travel should not postpone clinically important neoadjuvant treatment merely to have surgery performed abroad.
Frequently Asked Questions for International Patients in India about Breast Cancer
1. Is mastectomy safer than lumpectomy?
For appropriately selected early cancers treated with indicated radiation, breast conservation provides comparable survival.
2. Does every breast cancer need chemotherapy?
No. Need depends on subtype, stage, recurrence risk and sometimes genomic testing.
3. What are ER and PR?
Hormone receptors that predict benefit from endocrine therapy.
4. What is HER2-positive breast cancer?
A biologically defined subtype that can respond strongly to HER2-targeted treatment.
5. What is triple-negative breast cancer?
Cancer lacking ER, PR and HER2; chemotherapy is central and immunotherapy is used in selected settings.
6. Why might chemotherapy be given before surgery?
To shrink disease, treat systemic risk early and measure treatment response, especially in selected HER2-positive/TNBC cases.
7. What is a sentinel-node biopsy?
A procedure sampling the first draining axillary nodes to stage many clinically node-negative cancers.
8. Does every positive node require full axillary dissection?
No. Modern treatment allows omission in selected situations.
9. Can I preserve my breast?
Often yes, depending on tumour extent, breast size, genetics and ability to receive radiation.
10. What is oncoplastic surgery?
Cancer removal combined with breast reshaping to improve conservation and cosmetic outcome.
11. Can reconstruction be done with mastectomy?
Yes, either immediately or later using implants or the patient's own tissue.
12. Will I need radiation after mastectomy?
Possibly. Node-positive, large or other high-risk disease can still require post-mastectomy radiation.
13. What does breast cancer surgery cost in India?
Many standard operations broadly fall around US$3,500-8,000; reconstruction can increase cost.
14. How much can India save?
Major surgery/radiation can show substantial private self-pay savings; branded drug savings vary widely.
15. How long should I stay in India?
Often about 2-4 weeks for uncomplicated surgery; reconstruction or additional treatment can require longer.
16. Can I continue chemotherapy at home?
Usually, if the exact regimen and drugs are available and local oncology follow-up is arranged.
17. Do I need genetic testing?
Selected patients do based on age, family history, tumour subtype and other criteria.
18. What is a genomic test?
A tumour-based assay that can help estimate recurrence/chemotherapy benefit in selected hormone-sensitive early cancers.
19. What records should I send before travel?
Pathology with ER/PR/HER2, breast imaging and all prior treatment/genetic reports.
20. What matters most before booking surgery?
Confirm subtype, stage and whether surgery should occur before or after systemic therapy.
21. Can I travel on my own for breast cancer treatment?
It is strongly advisable to bring a companion. Drains, arm restrictions, fatigue and decisions about further treatment are easier with support, and a companion can help if chemotherapy or radiation starts in India.
22. What if my surgeon wants to start with surgery but my subtype suggests treatment first?
Ask for the reasoning in writing and for review by a multidisciplinary tumour board. A second opinion is reasonable, and the sequence should be settled before any operation is booked.
23. Is a lower price a reason to choose a centre?
No. Compare the clinical plan, the team's breast-specific experience, the radiation and systemic-therapy access and the contingency for complications first. A low surgery price that excludes drugs and radiation can end up costing more.
24. Can my home oncologist follow me after surgery?
Often yes, but only if they have agreed in advance and received the final pathology with receptors, operative report and treatment recommendations. Confirm this before you leave India.
Breast Cancer Checklist for International Patients in India
Diagnosis
- Core biopsy
- Histology/grade
- ER
- PR
- HER2
- Axillary assessment
- Clinical stage
- Genetic testing if indicated
Treatment decision
- Surgery-first vs neoadjuvant
- Breast conservation
- Oncoplastic option
- Mastectomy indication
- Sentinel/axillary plan
- Reconstruction timing
- Radiotherapy need
- Lymphedema prevention plan
Systemic treatment
- Chemotherapy
- HER2 therapy
- Immunotherapy
- Endocrine therapy
- Genomic assay if indicated
- Fertility preservation
- CDK4/6 or other targeted therapy if indicated
- Bone-modifying therapy if indicated
Centre
- Breast surgeon
- Medical oncology
- Radiation oncology
- Breast imaging
- Pathology
- Plastic/reconstructive surgery
- Genetics
- Lymphedema rehabilitation
Cost
- Surgery
- Sentinel tracer
- Axillary surgery
- Reconstruction/implant
- Pathology
- Systemic drugs
- Radiation
- Genetic/genomic tests
- Complication exclusions
Before return
- Final pathology
- Operative report
- ER/PR/HER2
- Medication
- Drain/wound plan
- Adjuvant plan
- Radiation plan
- Rehabilitation
- Surveillance imaging
- Home oncologist
Final Perspective
Modern breast cancer care is increasingly personalized. The goal is not to perform the largest operation but to combine adequate local surgery with subtype-directed systemic therapy, appropriate radiation and thoughtful preservation or reconstruction of the breast and axilla. Neoadjuvant treatment has become especially important because response can guide subsequent treatment in HER2-positive and triple-negative disease.
India offers comprehensive breast oncology, oncoplastic surgery, reconstruction, modern radiation and systemic therapies with substantial private self-pay cost advantages for many services. International patients should obtain a multidisciplinary treatment sequence before travelling and compare the entire pathway rather than the surgery price alone.
Send your biopsy and pathology reports with ER, PR and HER2 results, mammogram, ultrasound and MRI images, any staging scans, node biopsy, genetic or genomic reports and details of any treatment already given. You will receive a preliminary opinion covering the subtype and stage, whether treatment should begin with surgery or systemic therapy, whether breast conservation or reconstruction is realistic, the radiotherapy and systemic-therapy plan, the stay in India, an itemized cost estimate and a follow-up plan, so you can decide with a clear picture in hand.
Sources
- 1. National Cancer Institute - Breast Cancer Treatment: https://www.cancer.gov/types/breast/treatment
- 2. American Cancer Society - Surgery for Breast Cancer: https://www.cancer.org/cancer/types/breast-cancer/treatment/surgery-for-breast-cancer.html
- 3. Government of India - Indian Visa Online (e-Medical Visa and e-Medical Attendant Visa): https://indianvisaonline.gov.in/evisa/
Important Medical Note. This guide provides general educational information and does not replace individualized assessment by a qualified breast cancer multidisciplinary team. Surgery type, neoadjuvant/adjuvant therapy, receptor-directed treatment, reconstruction, radiotherapy, cost and travel timing must be determined from the patient's pathology, stage, imaging, genetic risk, medical fitness and treatment goals.